Cochlear / Remote Care
Designing care beyond the clinic.
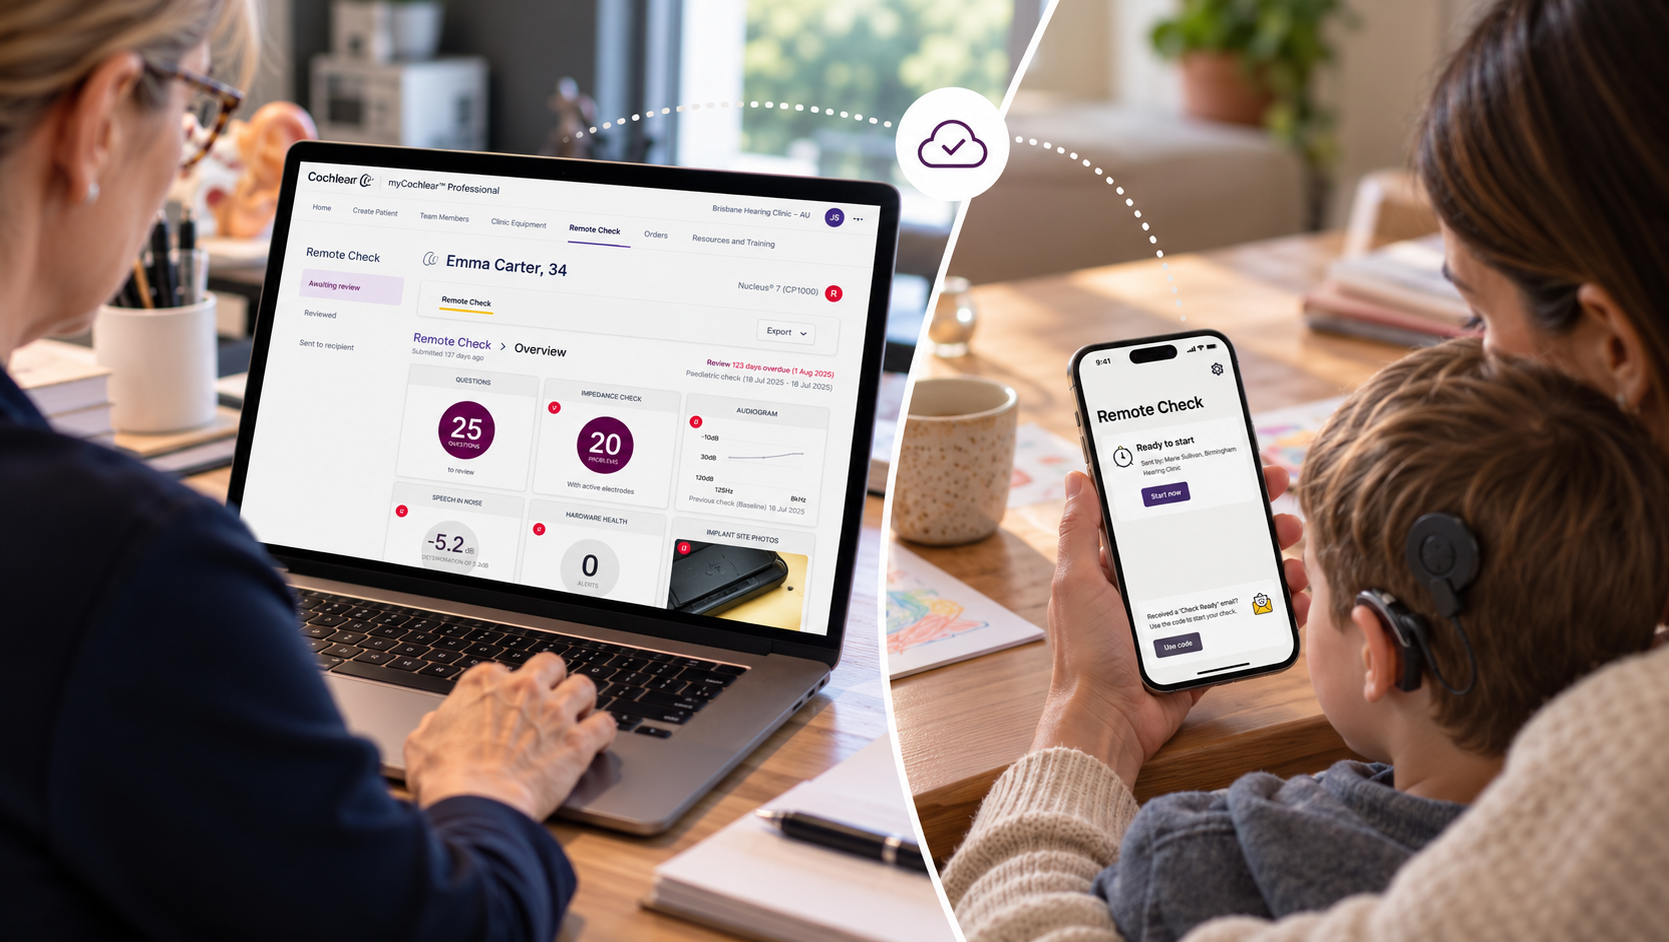
Helping evolve an early clinical trial into a connected healthcare service for clinicians and cochlear implant recipients.
When I joined Cochlear’s Remote Care programme, it was being trialled in a small number of UK clinics. Enrolment, clinical workflows and the recipient experience still needed to work together before the service could support wider use.
I first designed clinician-managed enrolment. My work then expanded across the clinician portal, recipient research and remote hearing assessments.
Working with clinicians, engineers and product teams, I helped connect the Nucleus Smart App, myCochlear Professional and hearing technology into a service that could work in clinical practice.
- Role
- Senior UX / Product Designer
- Focus
- Product design, UX research, service design
- Experience
- Clinician portal, recipient enrolment, Remote Check assessments and connected workflows
- Products
- myCochlear Professional / Nucleus Smart App
From trial to product
A check completed at home still needed to fit a clinical workflow. Enrolment, scheduling, results and follow-up had to connect across the recipient app, clinician portal and supporting systems.
01 / Clinician experience
Designing around clinical decisions.
Clinicians needed more than access to results. They needed to judge reliability, understand change over time and decide what to do next. The redesign connected those decisions to a clearer portal workflow.
Understanding how clinics actually worked
Before Remote Care could expand beyond its early clinical trials, we needed to understand how it would fit into everyday clinical practice.
I visited clinics across Europe, working with clinicians to understand their workflows, clinical requirements and the challenges of delivering care remotely.

Designing a connected enrolment experience
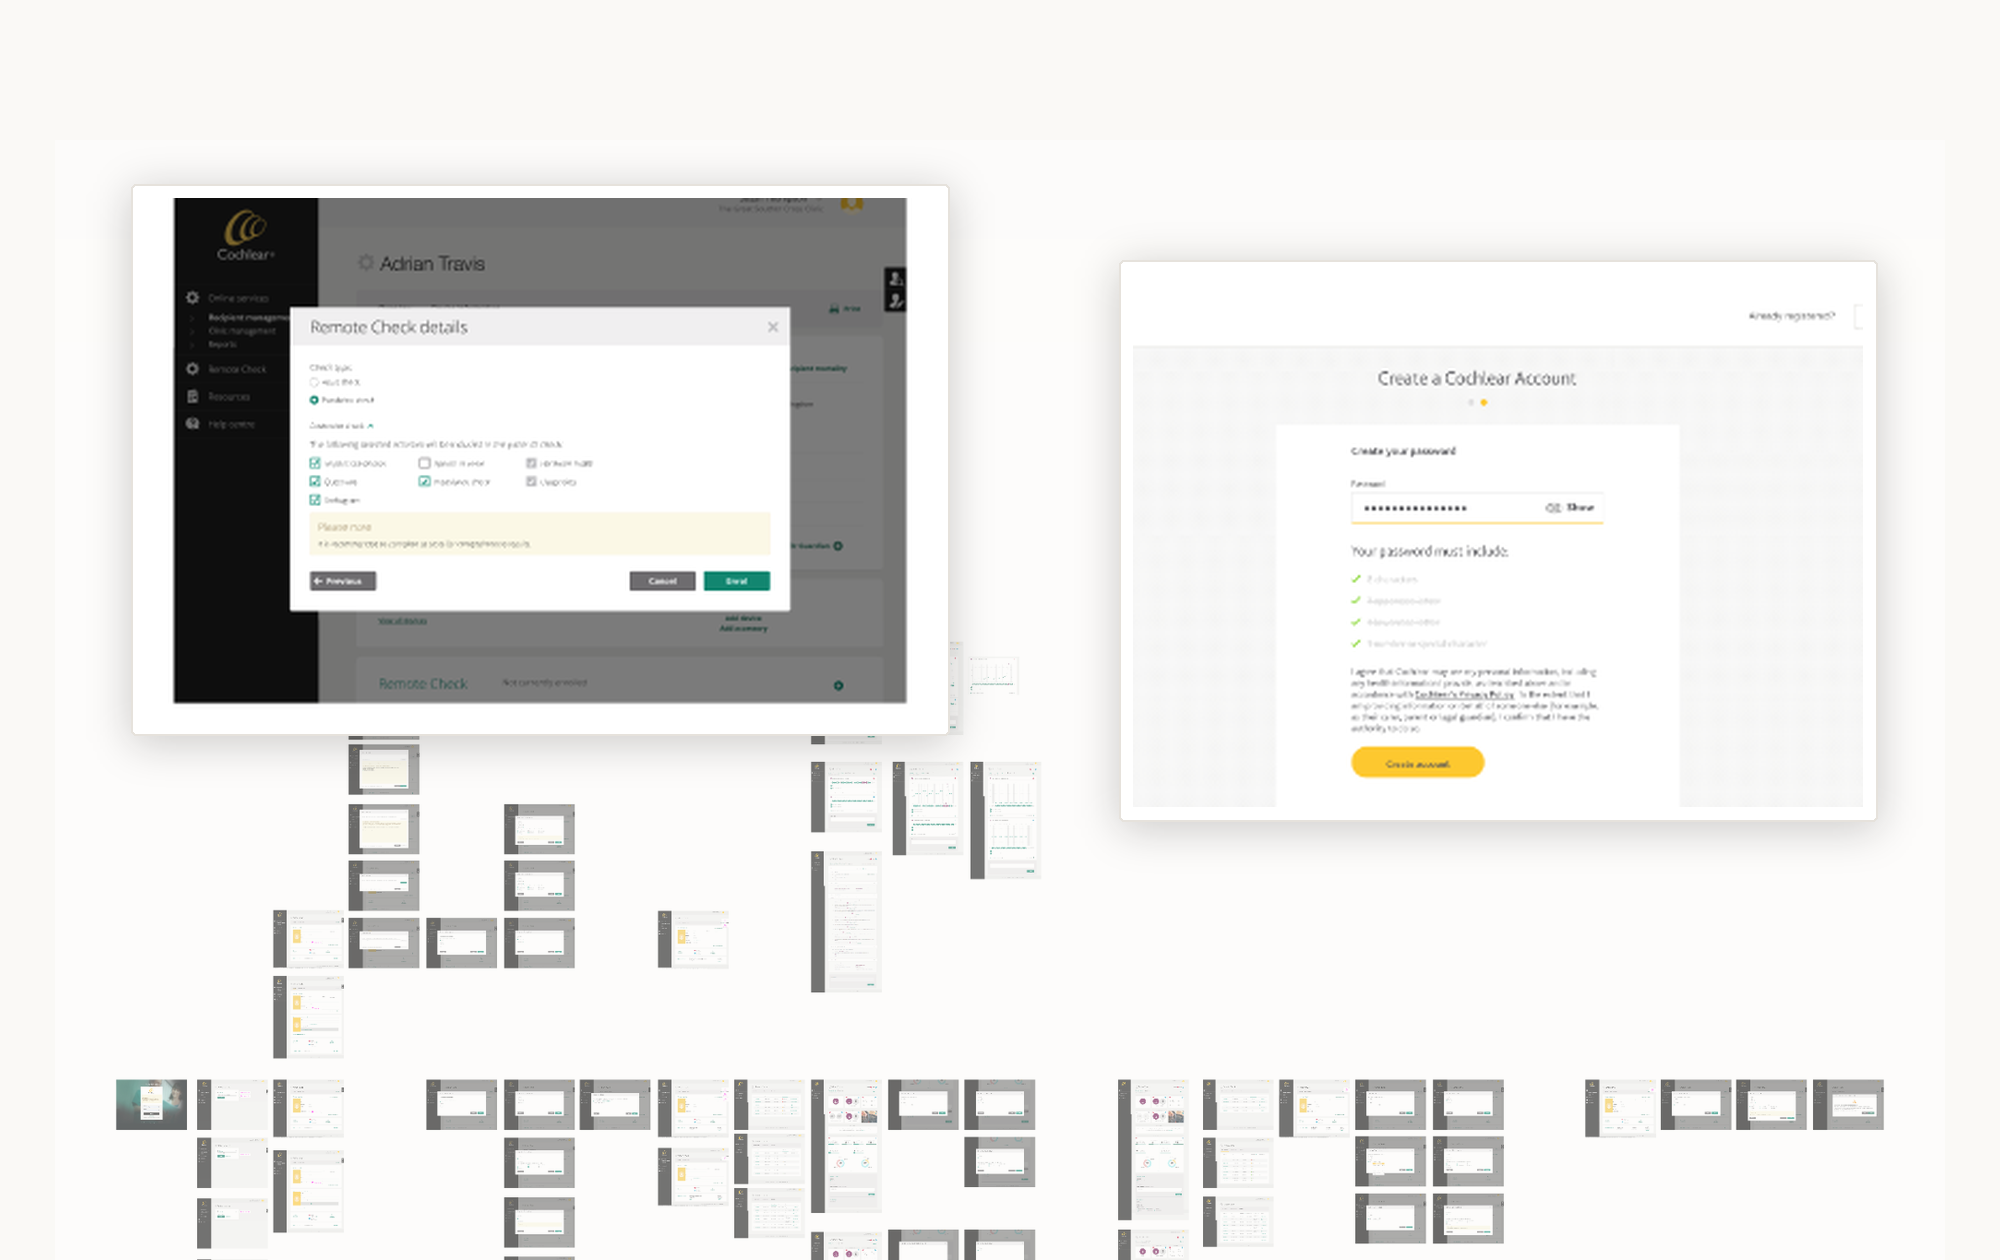
Enrolment was still handled manually by Cochlear. I designed a clinician-managed journey spanning myCochlear Professional, account registration, invitations and the Nucleus Smart App.
It had to account for adult and paediatric recipients, caregiver communications, verification and assessment scheduling. Research also showed that one fixed set of activities would not suit everyone.
I enabled clinicians to select activities and configure baseline and follow-up assessments within their existing workflow.
Making clinical work manageable
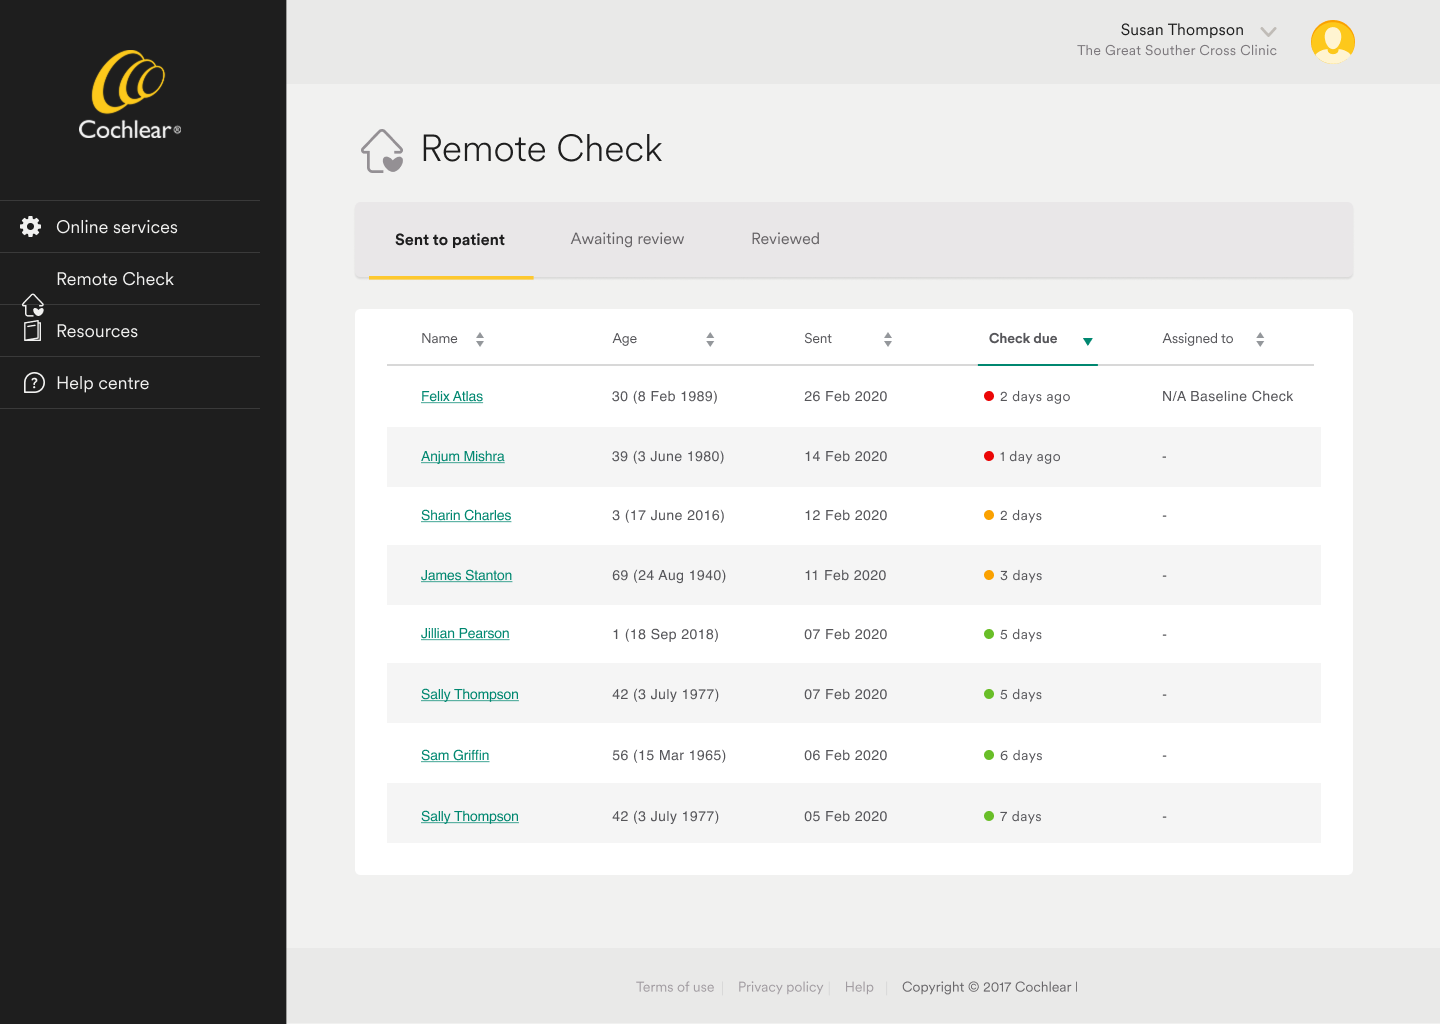
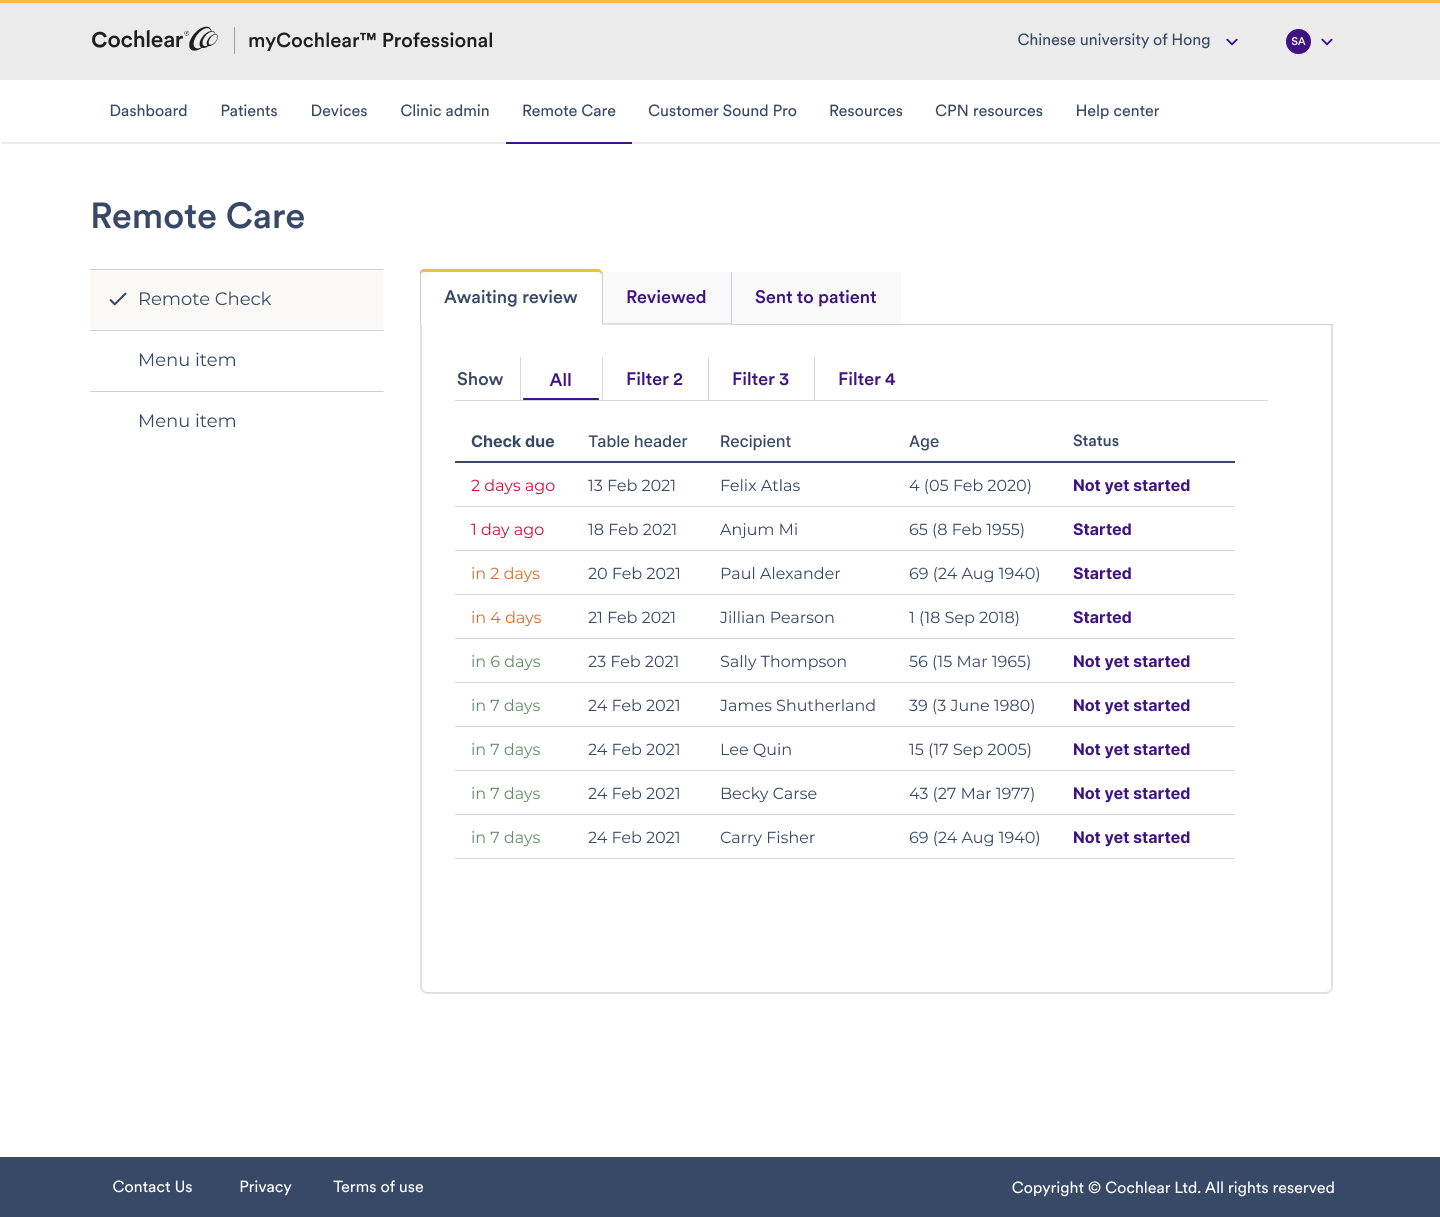
Clinicians needed to see which assessments were awaiting review, overdue or still in progress. The existing experience made those priorities hard to scan.
I organised Remote Checks into clearer workflows, then refined statuses, due dates, summaries and notifications so clinicians could identify what needed attention and access completed checks.
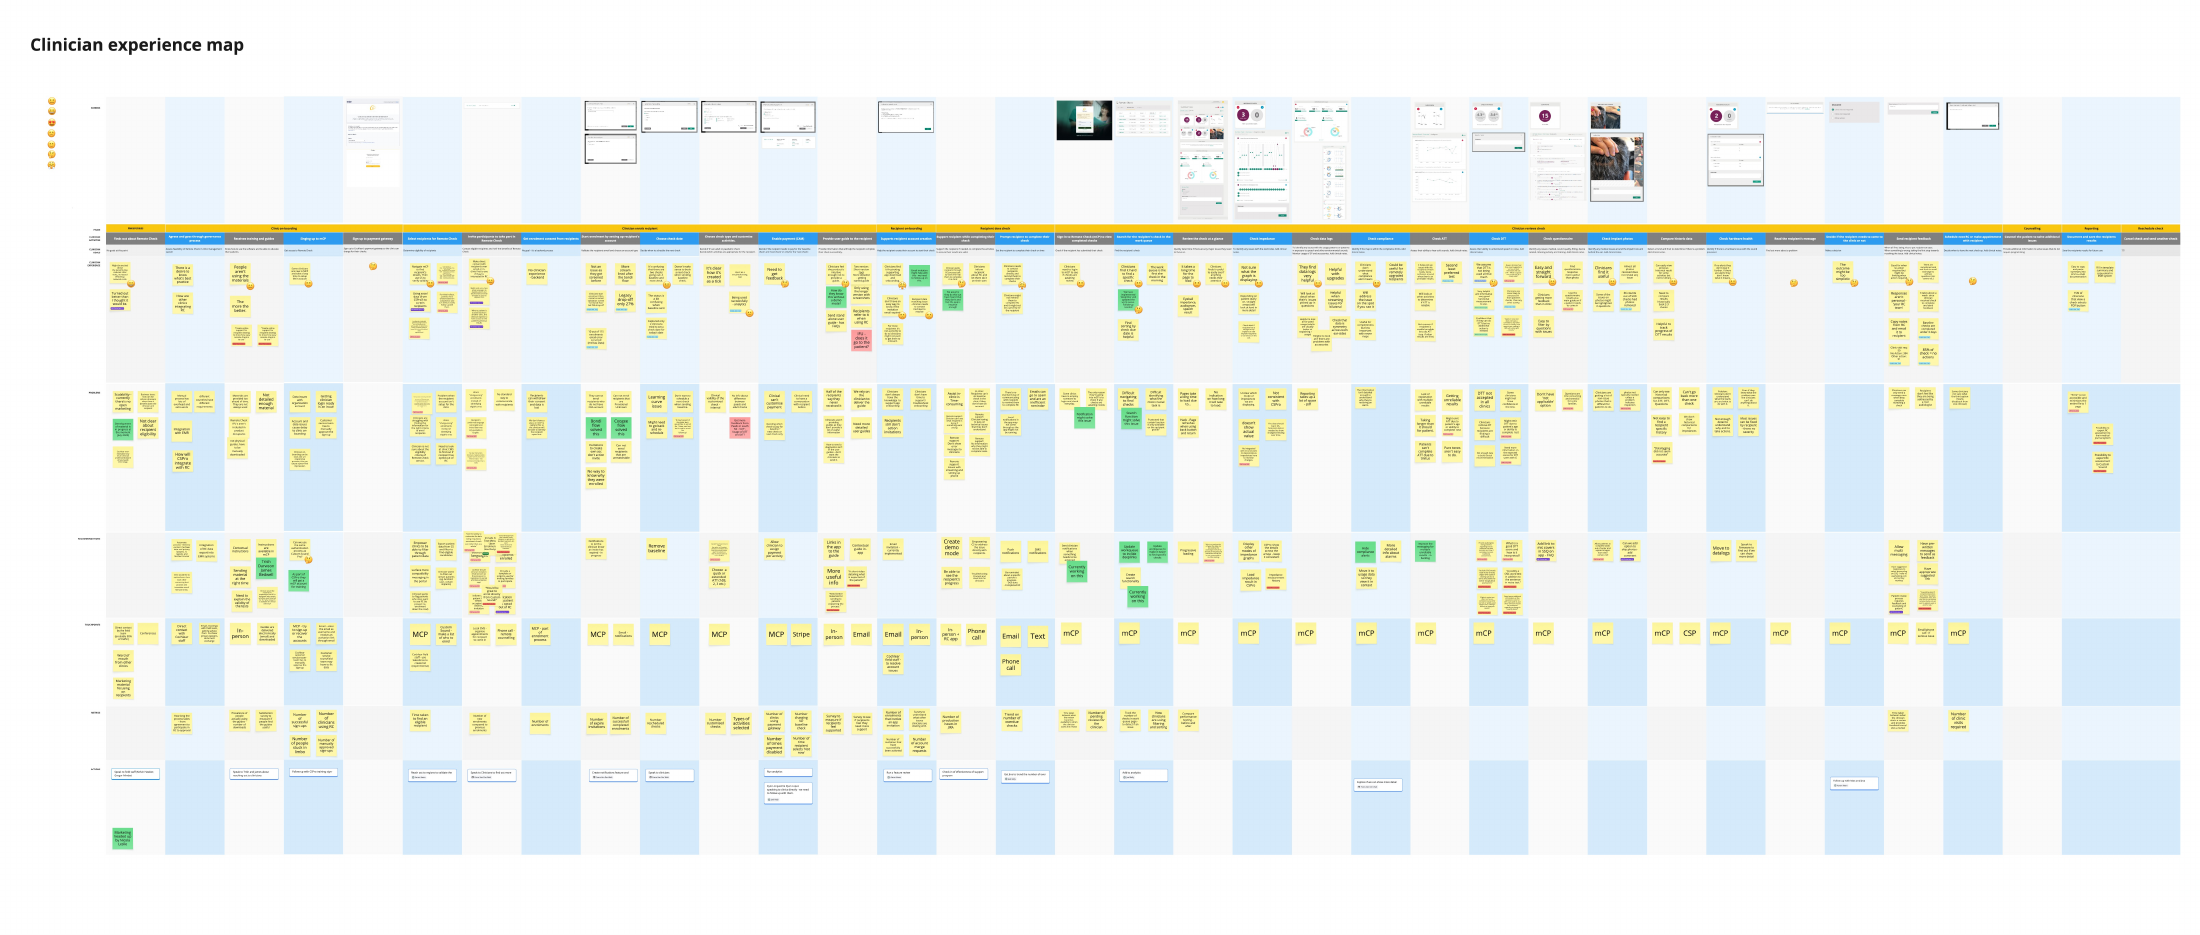
Understanding the complete clinical journey
As Remote Care evolved, I led further research with clinicians to understand how the service fitted into their everyday workflows and where they encountered friction.
I mapped the end-to-end clinical experience, from enrolling recipients and scheduling assessments to reviewing results and determining appropriate follow-up care.
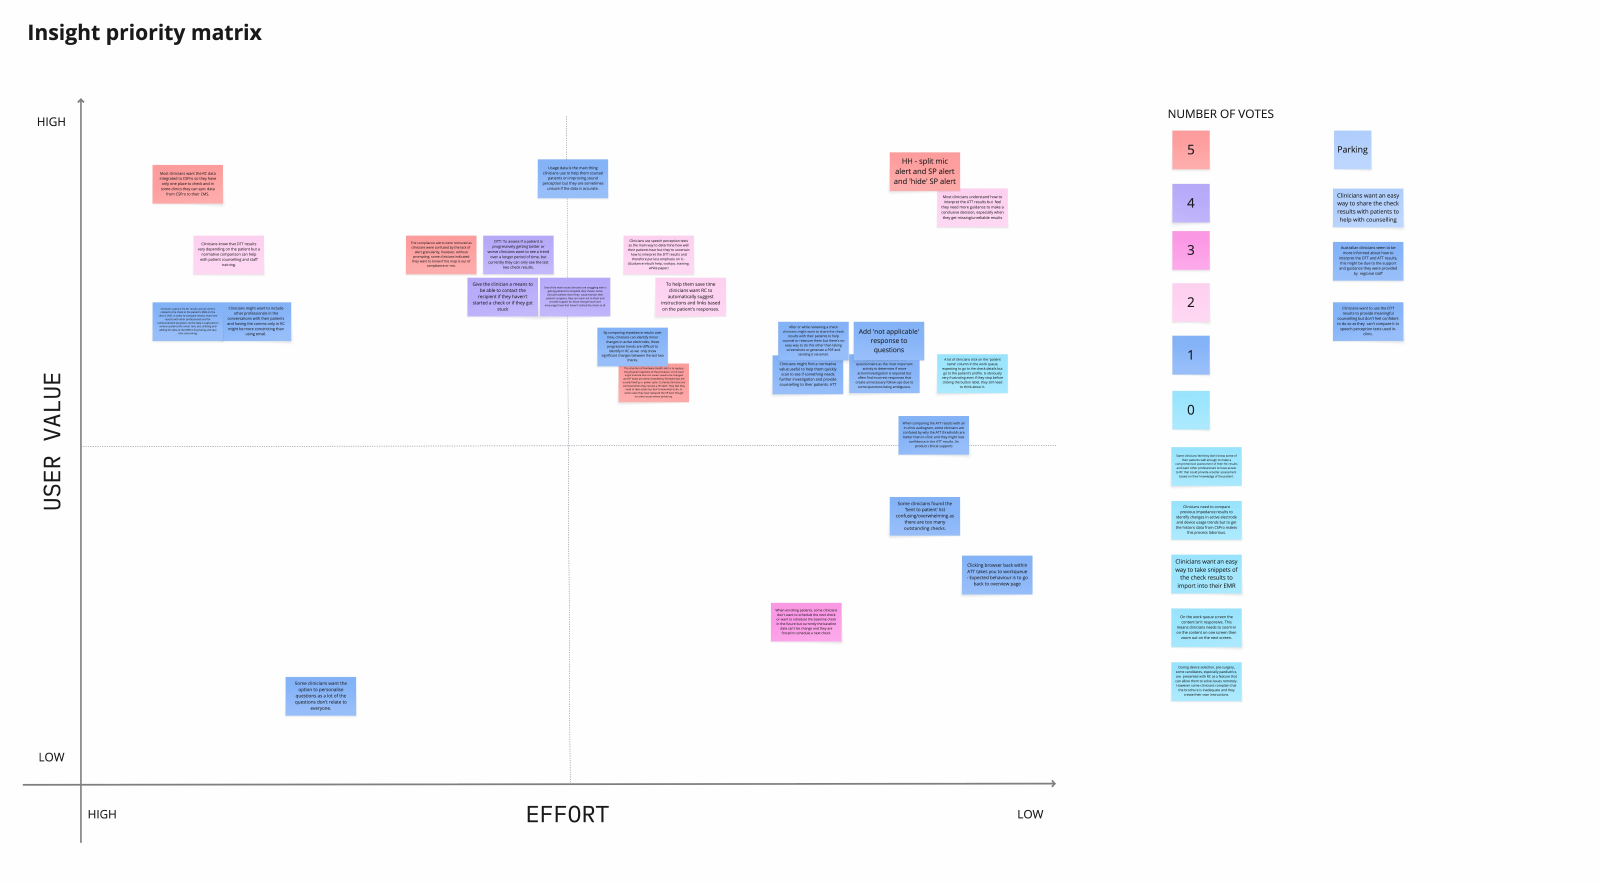
I synthesised the research through affinity mapping and worked with stakeholders to prioritise opportunities based on clinical needs, user value and implementation effort.
This helped establish a clearer direction for subsequent improvements, particularly around clinical workflows, result interpretation and decision-making.
Making clinical results easier to interpret
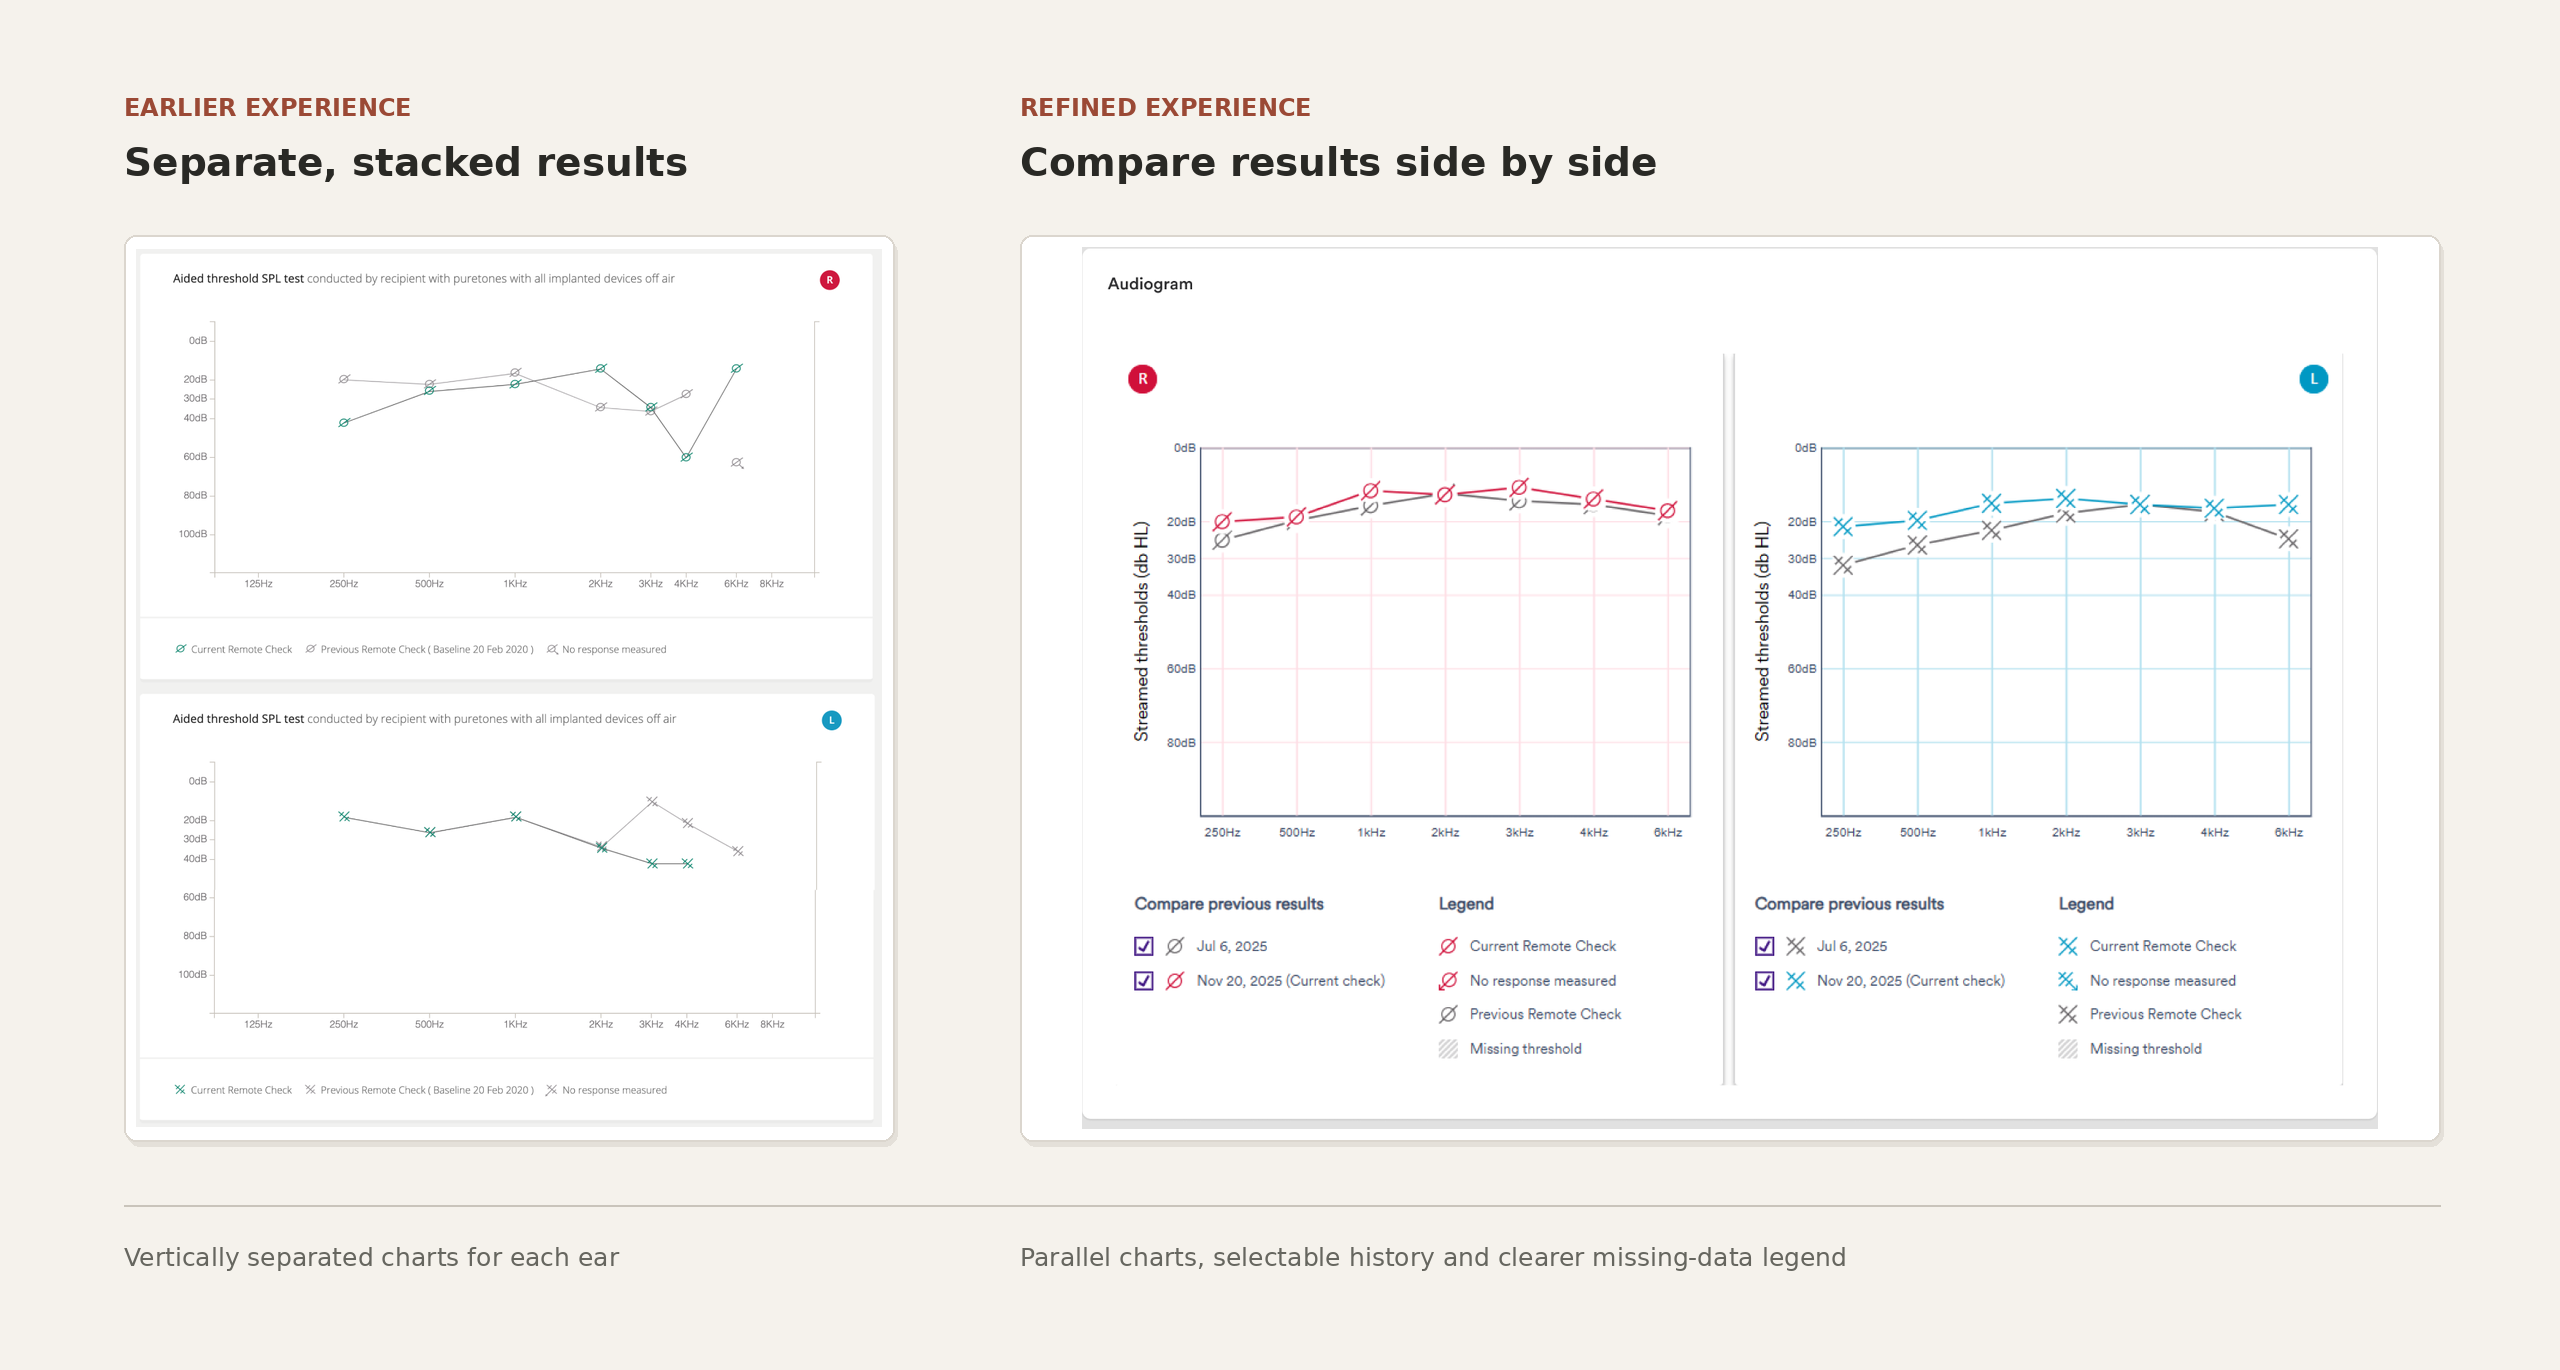
Clinical research revealed that interpreting Remote Check results wasn't always straightforward. Clinicians needed to compare assessments over time, identify changes and understand when results were incomplete or inconsistent.
I redesigned the audiogram experience to make this information easier to interpret.
The redesign introduced side-by-side visualisations for each ear, clearer threshold and frequency information, controls for comparing historical results, and improved explanations of missing data and unanswered thresholds.
Working closely with clinicians and technical teams, I translated complex clinical requirements into a more intuitive experience that supported clinical decision-making.
Making clinical data easier to trust
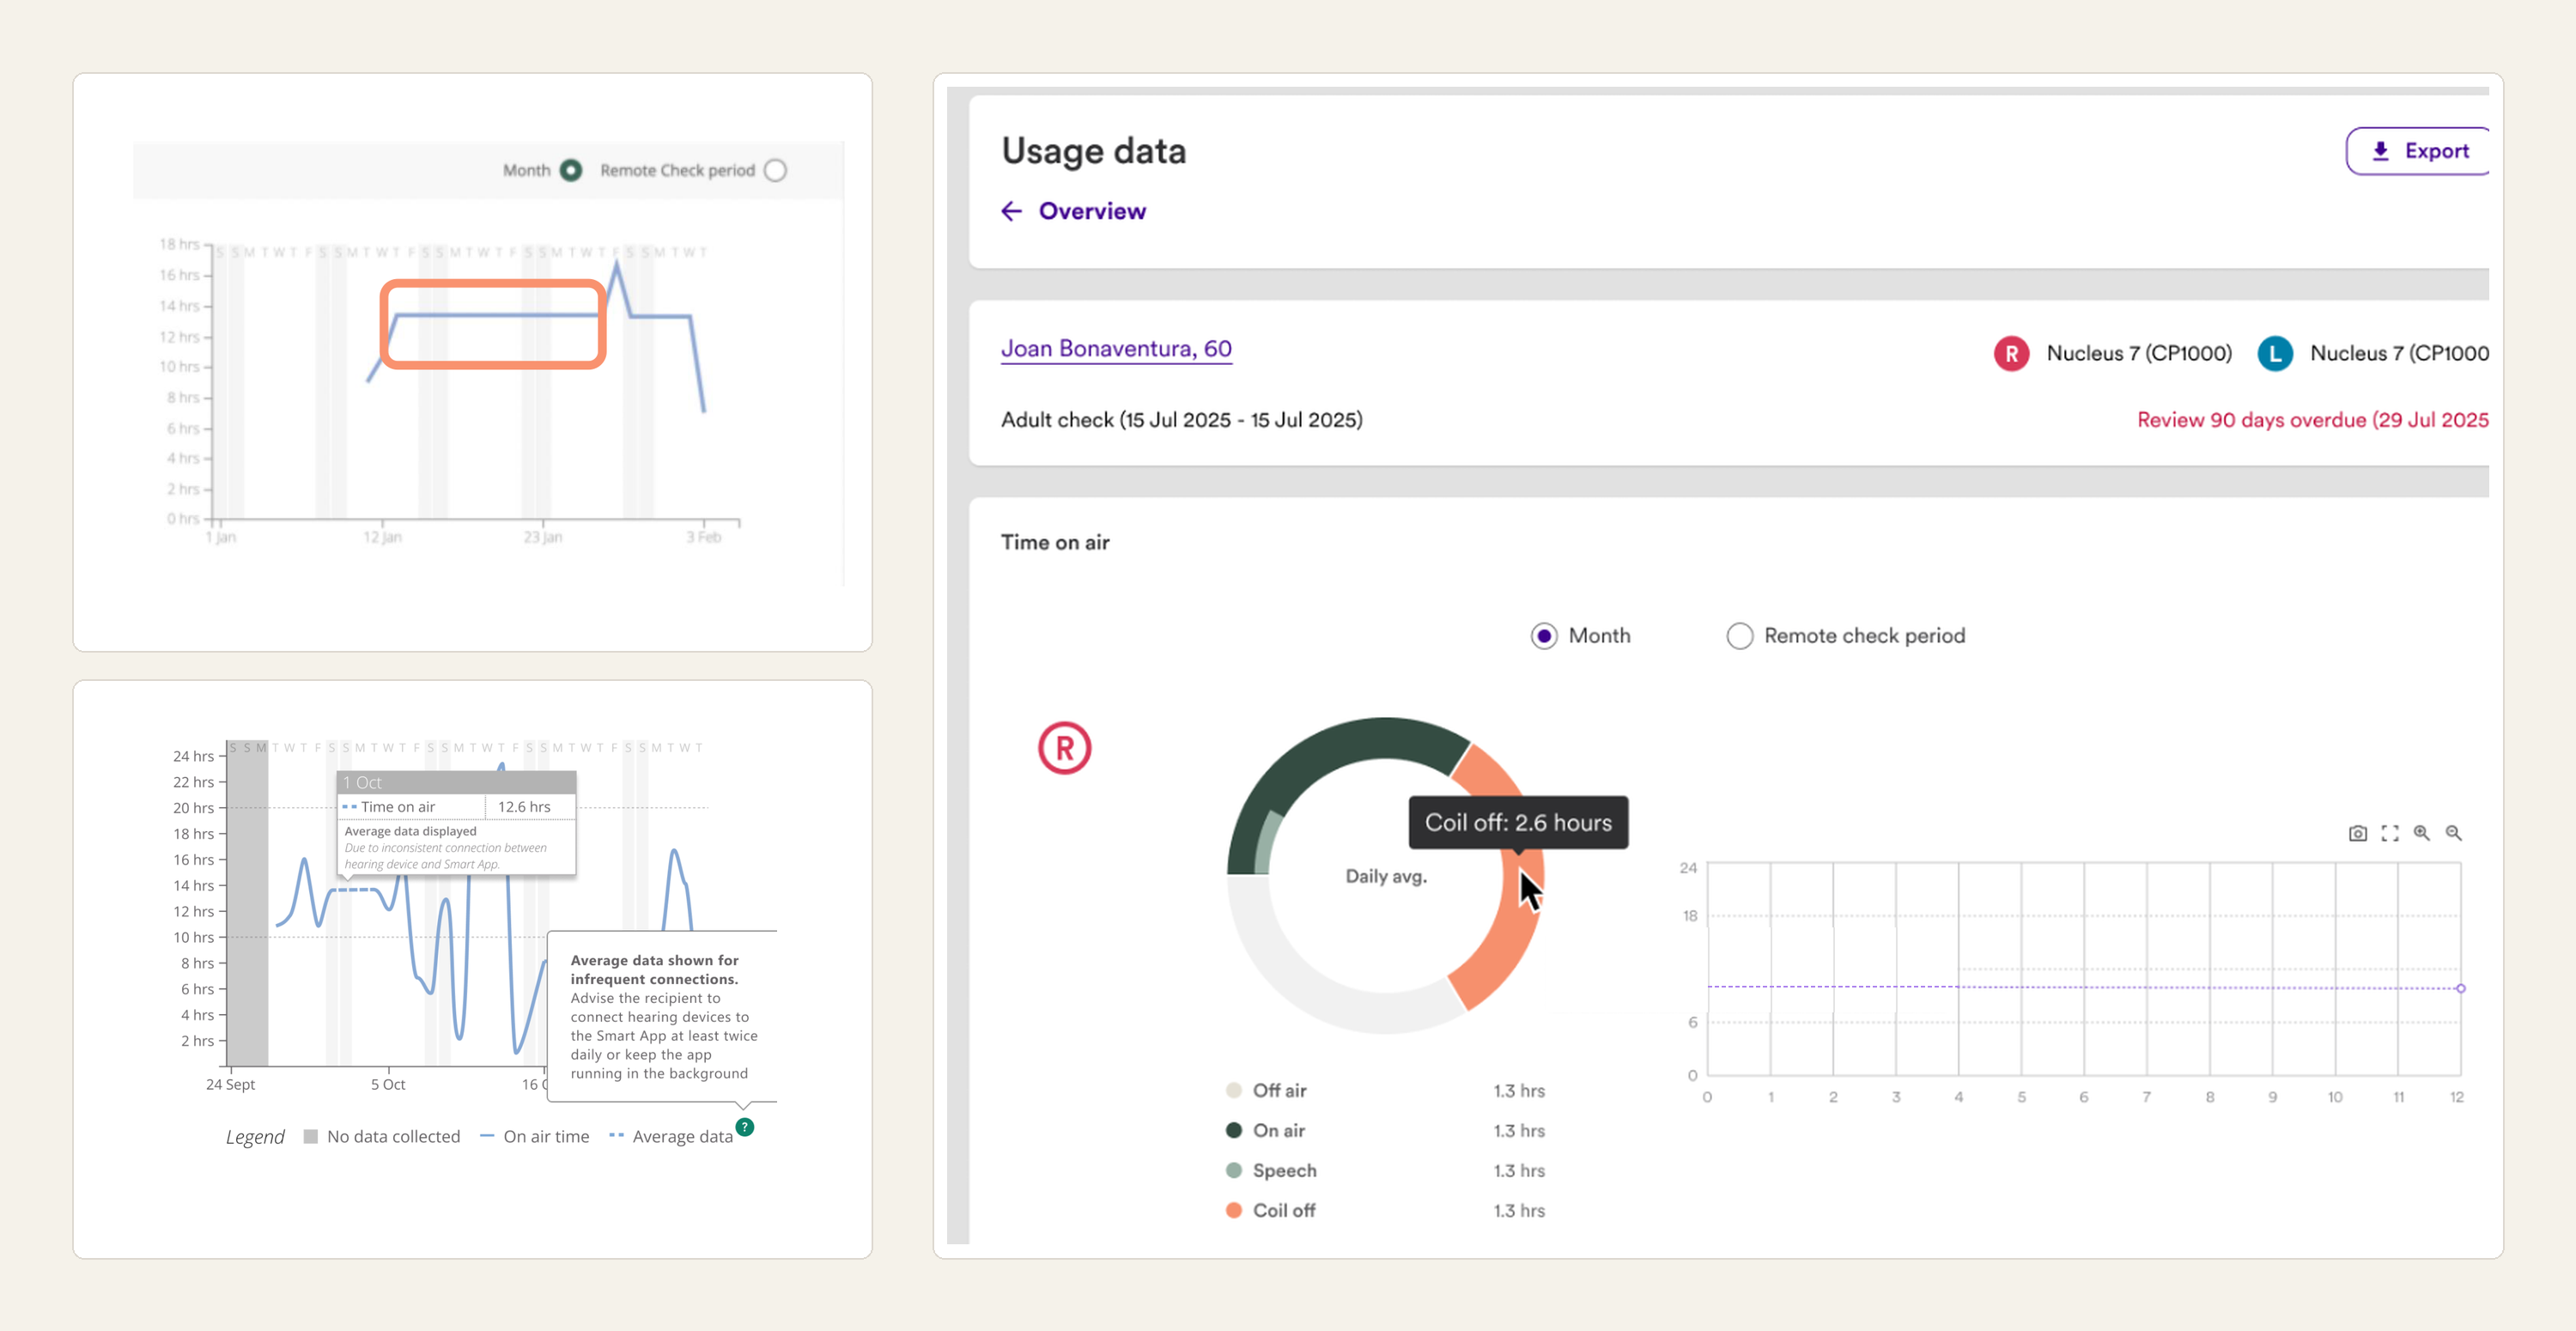
Sound processor usage data helps clinicians understand recipients' hearing behaviours, monitor progress and identify potential problems.
But the data wasn't always reliable. Inconsistent connections between the sound processor and Nucleus Smart App created gaps, while averaged data could misrepresent actual usage.
I conducted research with eight clinicians across Norway and the UK, exploring how they interpreted this information and evaluating alternative visualisations through interactive prototypes.
Working with clinical and technical teams, we explored more accurate calculations, clearer distinctions between recorded and averaged data, and better explanations of missing information.
The updated usage-data interface was implemented, helping clinicians better understand the information available when making care decisions.
Designing the systems behind connected care
Aligning teams around the problem
Remote Care sat alongside Custom Sound Pro and myCochlear Professional. Clinicians faced repeated sign-in, platform switching and fragmented care status while managing patients across clinics.
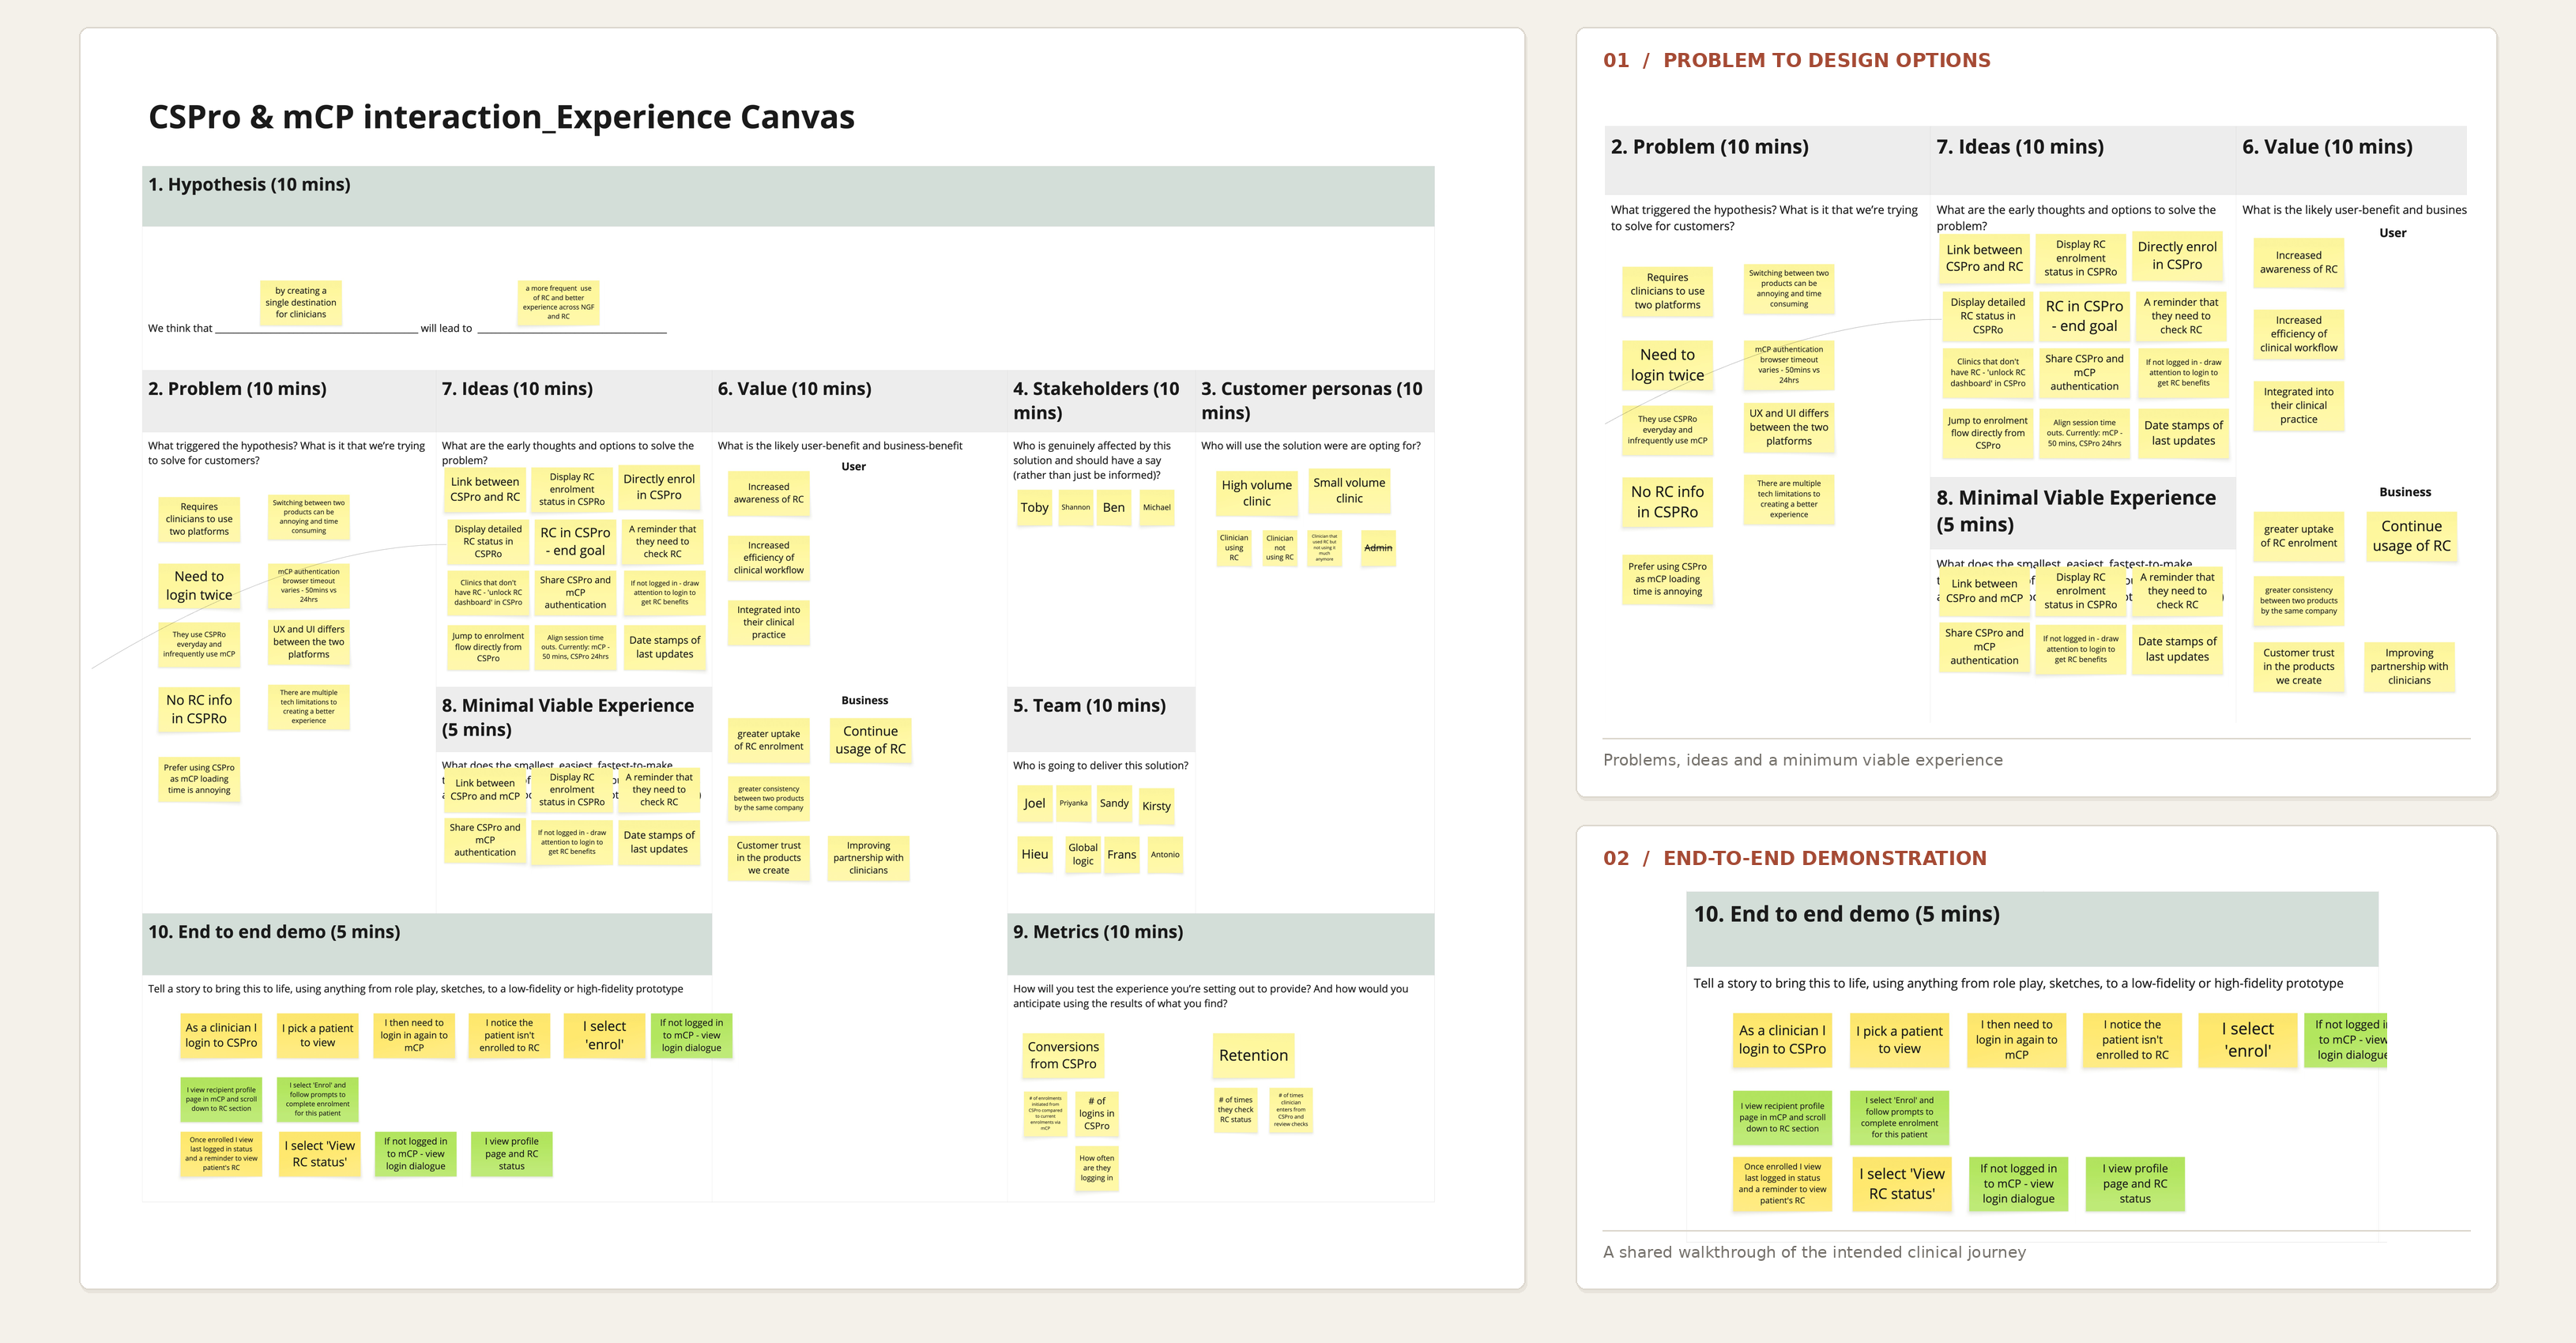
I introduced an Experience Canvas to work through those problems with clinical, product and engineering stakeholders. Together we challenged assumptions about authentication, where enrolment and results should appear, and how Remote Care could fit existing practice.
The canvas gave the team a shared problem definition and a way to compare design options before committing to implementation.
Turning complexity into connected workflows
I mapped end-to-end flows across clinicians, recipients and systems, including affiliated clinics, permissions, data sharing and consent. The work covered how clinicians request access to another clinic’s assessments and how recipients control that access.
Working with clinical, product, firmware and engineering colleagues, I translated the prioritised research into portal navigation, notifications, alerts and results presentation, including Digit Triplet Test context. These flows became a shared reference for delivery; the multi-clinic functionality was implemented.
I also designed recipient–clinician messaging states, including failed delivery, and contributed to US payment workflows.
02 / Recipient experience
Making Remote Check easier to complete at home.
Understanding where recipients were struggling
Remote Check was designed to help recipients complete hearing assessments at home. But not everyone was finishing their checks, and we needed to understand why.
I initiated an investigation into product usage data to understand how recipients progressed through their assessments, where they were dropping off and what might be getting in their way.
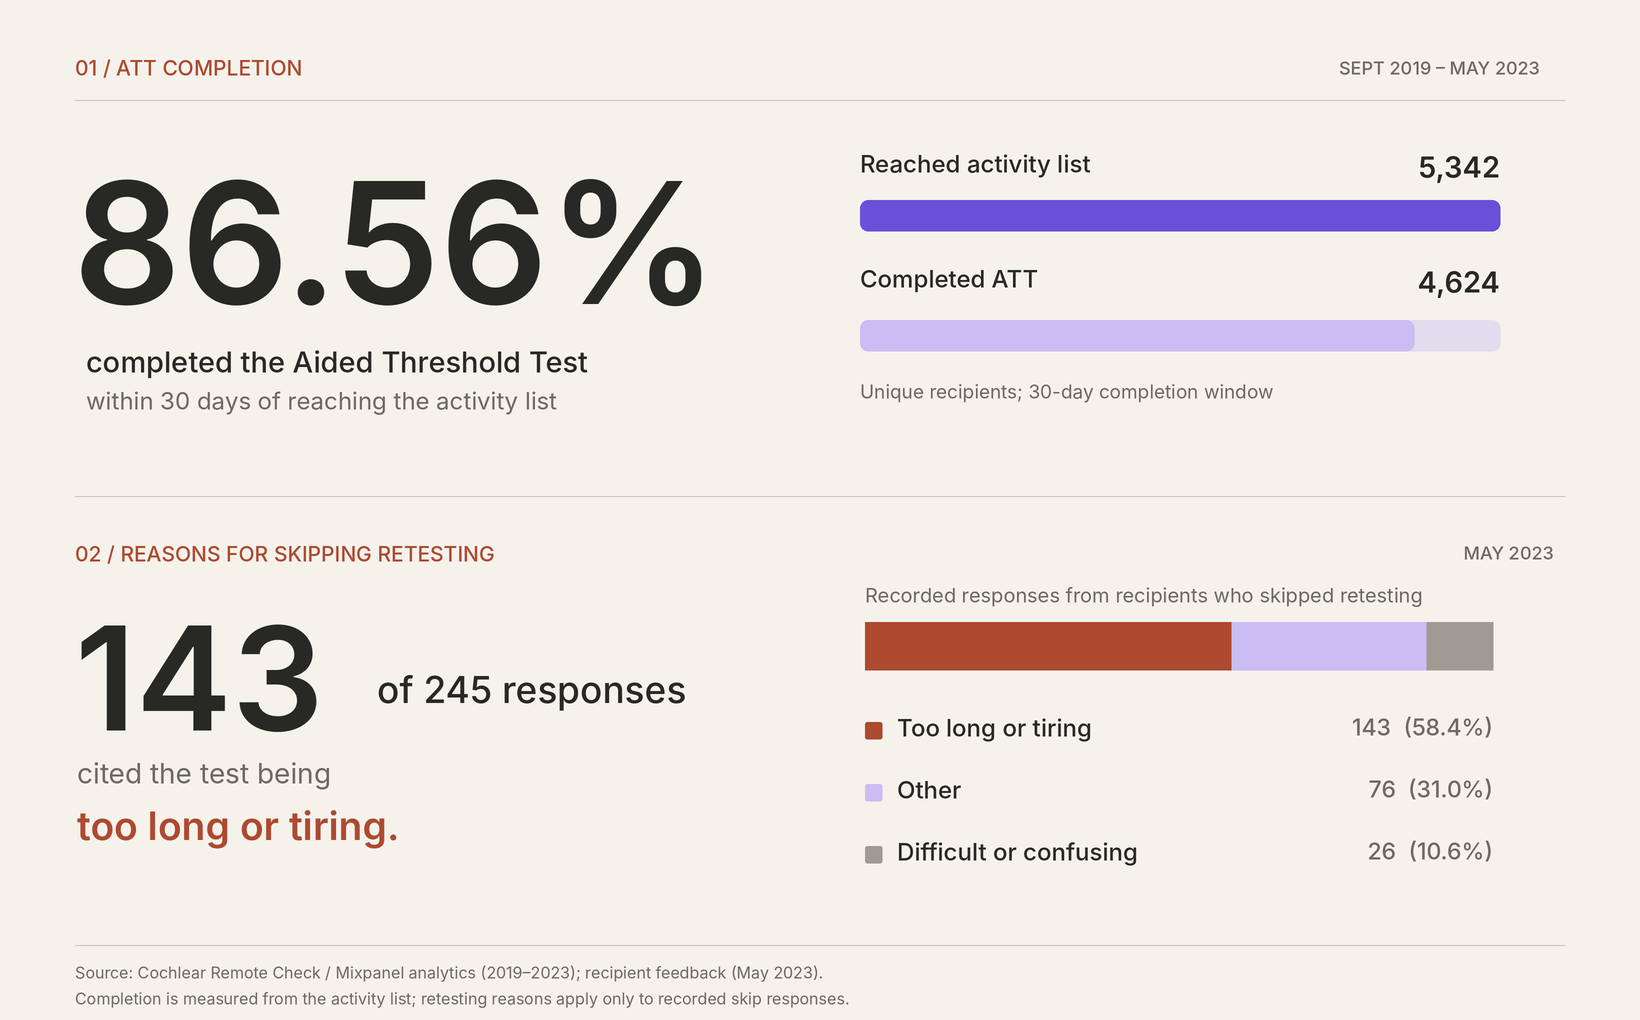
Understanding the experience behind the data
In 2023, I led research with 11 recipients, alongside audiologists and internal stakeholders. Watching people complete Remote Check showed what the analytics could not: how time, uncertainty and repeated interactions shaped the experience.
Those observations helped us separate difficulties with the surrounding journey from problems in the hearing test itself.


Fit the check into daily life
Recipients wanted to know how long a check would take and to continue later if interrupted.
Make progress and next steps clear
Visible progress and clear guidance mattered when completing assessments without a clinician present.
I synthesised the research findings and presented them to stakeholders, challenging existing assumptions and helping shape the next round of improvements to Remote Check.
One assumption remained: were some hearing-test responses labelled as false positives actually correct?
Rethinking the hearing test
Clinicians and technical specialists had assumed some very soft sounds were inaudible. I tested that assumption with recipients and validated that some could genuinely hear them.
That changed the design brief. Working with clinicians and engineers, I helped simplify the underlying ATT logic to shorten assessments and avoid unnecessary repetition, while also exploring a clearer interface concept.
Introduced larger 20 dB increments further from the hearing threshold, refining to 5–10 dB increments as the test approached the threshold.
Reduced unnecessary sound presentations and shortened retesting so recipients didn't need to repeat every frequency.
Explored a cleaner, more focused interaction with clearer Yes/No responses and reduced visual complexity.
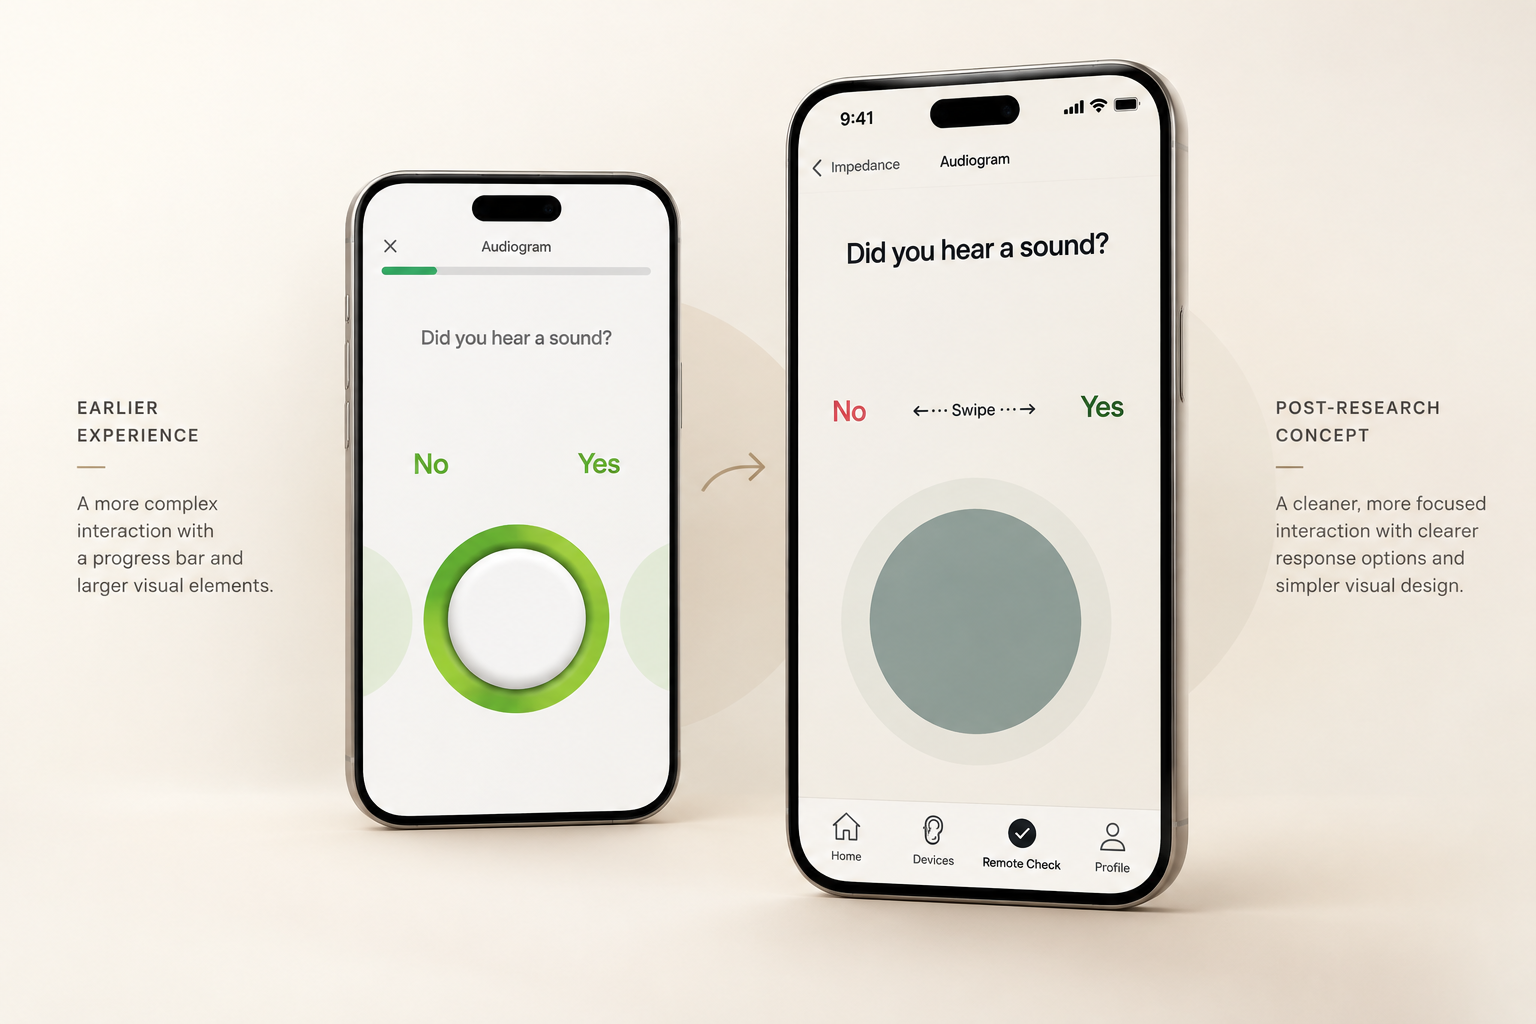
The redesigned testing logic was implemented, reducing unnecessary sound presentations and retesting. Subsequent usage data indicated faster completion times, although the original performance figures are unavailable.
The newer phone shown above is a post-research interface concept; the shorter testing logic was implemented.
Making connected care work in practice.
I connected clinical requirements, research and technical constraints across four parts of the service.
Put clinicians in control
I established clinician-managed enrolment across the portal, accounts, invitations and assessment setup.
Make work and results clearer
I improved assessment workflows and the presentation of audiogram and usage data to support interpretation.
Simplify the test itself
I helped change the ATT testing logic to reduce unnecessary sound presentations and retesting.
Work across clinical boundaries
I designed multi-clinic access, consent and cross-platform flows with clinical and technical teams.
I brought field research, technical collaboration and systems thinking together to make connected care workable across clinics, products and people’s lives.